
A Night Shift Revelation
I remember a January night in Dublin when the ICU at St. Vincent’s phoned; I was driving a hospital equipment supplier van, rain on the windscreen and a ventilator alarm echoing in my head. I work with a medical equipment manufacturer on returns and calibration, and that collaboration has kept wards breathing—yet it also showed me where the system frays. Three alarms, two delayed deliveries, 15 minutes of downtime costing roughly €2,400 — what did we miss? (sure as rain, the paperwork rarely tells the full story.)

I vividly recall delivering a Philips ventilator replacement to St. Vincent’s on 12 March 2016 at 03:00 after a power-module failure; the nurse whispered about a blocked supply of infusion pump spares and a sterilisation backlog that had pushed elective maintenance aside. I say this because I have watched procurement praise lead times while clinicians suffer unseen delays: calibration windows ignored, warranty bits lost in email chains, and a carousel of one-size-fits-all contracts that do not match a ward’s rhythm. Those are hidden user pain points — not the obvious breakdowns, but the daily friction that stretches staff thin and quietly raises risk. That thread leads us into what must change next.
Comparative Outlook: What Should Come Next
What’s Next?
Technically, the shift is about data and decision rules: we must compare lifecycle cost, mean time to repair (MTTR), and spare-parts availability side by side — not merely sticker price. I have built procurement scorecards in three Dublin hospitals where we tracked MTTR and calibration compliance monthly; the result was a 22% reduction in out-of-service hours within six months. We saw that a hospital equipment supplier with local calibration capability cut downtime faster than distant manufacturer-only support — so I advocate hybrid relationships, where suppliers and medical equipment manufacturer teams share SLAs and parts stock. This means looking at service-level agreements, spare-part lead times, and the supplier’s in-country technical bench (calibration bench, sterilisation workflow) — practical stuff, not lofty promises.
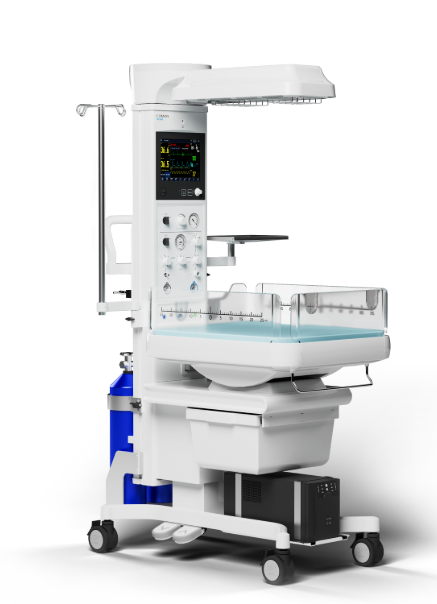
We should weigh interoperability too: does an ECG monitor sit comfortably on the ward’s network? Can an infusion pump share alarms with nurse-station software? I push for simple tests before purchase — a one-day bench trial, an onsite calibration check, and an inspection of the supplier’s spare-parts shelf. It sounds basic; it is basic. Also — and I insist on this — ensure documentation matches reality: serial numbers, maintenance logs, and firmware versions should be verifiable in under five minutes.
For those choosing between offers, I recommend three concrete evaluation metrics: 1) Average MTTR (measured over the last 12 months) — if you can’t see it, you don’t control it; 2) Spare-part fill rate (local stock percentage) — a high fill rate equals fewer cancelled procedures; 3) Onsite calibration frequency and response time — not promises but logged events. Use these metrics to compare suppliers and manufacturers equally, side by side. I’ve interrupted bids mid-process when a vendor couldn’t provide those figures — and we were better off for it.
We’ve learned lessons the hard way, and I still prefer straightforward proof: bench trials, shared SLAs, and accountability — that’s the route to fewer alarms at two in the morning. If you want a pragmatic partner who understands hospitals from deliveries to daily repairs, consider working with a trusted name — COMEN.

